

Static models stagnate, iterative models improve. Most precision dosing platforms deliver fixed population pharmacokinetic (popPK) models from the scientific literature, trained once on small datasets from one or two institutions and deployed indefinitely with little scrutiny afterwards.
At InsightRX, our continuous learning framework works differently: de-identified routine clinical care data flows continuously from hundreds of participating institutions in our network, where it is aggregated and used by our Data Science team to develop new models, improve existing ones, and help you select the best model for your patient.
This framework has produced several new adult vancomycin models, improvements to several published ones, and an update to our evidence-based model guidance engine, InsightRX Gemini.
Across the adult vancomycin patients in our network, a model InsightRX developed is now the best choice for roughly 45% of them, and an external model we improved is the best choice for another 40%.
Models from literature used unchanged in InsightRX Nova remain the best choice for only 15% of patients.
The shared problem: models are fit for the middle
Vancomycin PK varies substantially with sex, age, body size, and kidney function; however, this variation is not always well-represented in the development populations of popPK models. The median adult patient on vancomycin is around 64 years old, fewer than 1 in 10 are younger than 35, and patients at the extremes of body size or kidney function are few and far between.
A popPK model is fit to minimize error across its entire development population. Even though the model can account for effects of body size and kidney function, patients near the middle are more ubiquitous and are therefore described well while misspecification at the margins is tolerated. This is a recognized source of inequity in precision dosing, and it leaves specific patient groups underserved.
So how do we address this problem? The InsightRX Data Science team has developed three tactics:
- Build a specialized model to fill in the gaps
- Build a better general model
- Modify an existing model without refitting it
These three approaches answer the underlying problem in three different ways, each with their own strengths and tradeoffs.
Strategy 1: Build a specialized model to fill in the gaps
Younger adults typically clear vancomycin faster than older adults. Patients with low serum creatinine (sCr) may have low muscle mass rather than high kidney function, which can result in overestimated kidney function and drug clearance. And patients receiving continuous renal replacement therapy (CRRT) clear vancomycin through extracorporeal organ support as well as their own kidneys. Because most model development populations have few—if any—examples of these types of patients, general adult models tend to handle these groups poorly, making optimal dosing challenging compared to more typical patients.
So we developed new specialized models for each group to fill in the gaps with data from:
- 6,080 young adults aged 18–35 across 145 US hospital systems, contributing 19,071 serum vancomycin levels.
- 2,354 adults with sCr at or below 0.8 mg/dL across 122 US hospital systems, contributing 6,729 serum vancomycin levels.
- 1,685 adults across 91 US hospital systems with 574 of them receiving CRRT, contributing 5,084 serum vancomycin levels.
In InsightRX Nova these are the Brooks young adult, Brooks low sCr, and Tong CRRT models, and each outperformed the alternatives available for its population. The young adult and low sCr models had higher accuracy, lower error, and comparable bias to existing general adult models, and performed consistently well in an external evaluation of 384,876 patients, even outside the specific subpopulations on which they were developed. The CRRT model showed higher accuracy, lower error, and lower bias than five published hemodialysis models we tested in an external evaluation of 724 hemodialysis and nonhemodialysis patients.
Strategy 2: Build a better general model
Constructing specialized models for underrepresented populations is often an intuitive, effective solution. However, this does not negate the utility of general models that can serve a broad segment of patients. In fact, we’ve previously shown that a well-specified general model can even outperform specialized models for the target population in pediatric oncology patients.
So what separates a well-specified general model from a poorly specified one? Three things:
- Development population: Models built on small convenience samples that cluster around a central mode and thin out fast in every direction will naturally perform poorly at the edges. Models built on large, diverse samples with representation across the full clinical range of important characteristics like sex, age, body size, and kidney function are more likely to perform equitably across patients.
- Model structure: Once a balanced and representative data set has been constructed, the next step is to create a model that accurately describes drug PK across the full clinical range to optimize dosing for a broad segment of patients.
- External evaluation: Even once we have developed a promising model, we need to demonstrate its predictive abilities for its intended use before applying it in the clinic. That means looking past a single headline number: aggregate accuracy and error are averages, so a model can look strong overall while performing poorly for exactly the patients who are hardest to dose.
Thanks to our large network of participating institutions, InsightRX is uniquely positioned to develop and provide general popPK models that follow these principles for a variety of drugs, ranging from infectious diseases to oncology to bone marrow transplant (BMT). Our collaboration with the BMT specialists at the University of California, San Francisco (UCSF) and other institutions has built a track record of this work within the BMT space—refining and expanding MIPD for busulfan, tacrolimus, fludarabine, thiotepa, melphalan, and more.
Most recently, we applied these principles in a novel way to create a new general adult vancomycin model, designated McCarthy 2026 in InsightRX Nova. Here’s how.
The development population is where our network mattered most
Most popPK models are built from whatever patient data happen to be available. Because certain patients tend to be over-represented in the clinic, model development populations tend to cluster around a single mode. For example, patients with renal insufficiency tend to be older, patients with leukemia tend to be younger, and so forth. However, with hundreds of institutions contributing data, we could create a data set that better captured human diversity. We sorted 549,171 patients treated across 304 US healthcare organizations into 504 strata spanning every combination of sex, age group, BMI category, and kidney function category, then capped how many patients any one stratum could contribute.
The result was a deliberately balanced sample spanning all combinations of sex, age, body size, and kidney function, with approximately equal representation of every subpopulation defined by these characteristics. This data set covered 488 of the 504 possible strata, and 411 of these strata reached the cap, meaning even unusual combinations of sex, age, body size, and kidney function had enough patients to inform the fit, without the model overfitting to the central mode.
A balanced sample makes a balanced model
A sample spanning the full clinical range only helps if the model can describe what it contains. Three features distinguish the McCarthy 2026 model from most previously published adult vancomycin models, and we could only fit them because our sample was well represented at the extremes:
- Body size was scaled on fat-free mass rather than total body weight, which avoids the clearance overestimation that total-weight allometry produces in patients with obesity.
- Age was used to predict both clearance and central volume. It improved the fit on clearance even though the CKD-EPI eGFR equation already contains an age term—a residual effect of age on vancomycin clearance that the equation does not capture on its own.
- Kidney function was given a bend rather than a single curve: the effect of CKD-EPI eGFR on clearance changes slope at 90 mL/min/1.73 m2, rising more steeply above that point. We identified the breakpoint empirically, but it is physiologically sensible: it marks the lower boundary of normal kidney function. Above it, clearance rises quickly in patients with augmented renal clearance, a group at elevated risk of underexposure on standard dosing. Against an otherwise identical model using a single curve, the bend reduced population prediction bias in that group by about a third.
The gains held up in patients the model never saw
In external evaluation against six published adult models, the McCarthy 2026 model achieved the lowest prediction error (NRMSE) and highest accuracy for both population and individual predictions, with comparable bias (MPE) to other well-performing models. More to the point, that performance held up evenly across age, body size, and kidney function rather than concentrating around the patients in the middle.
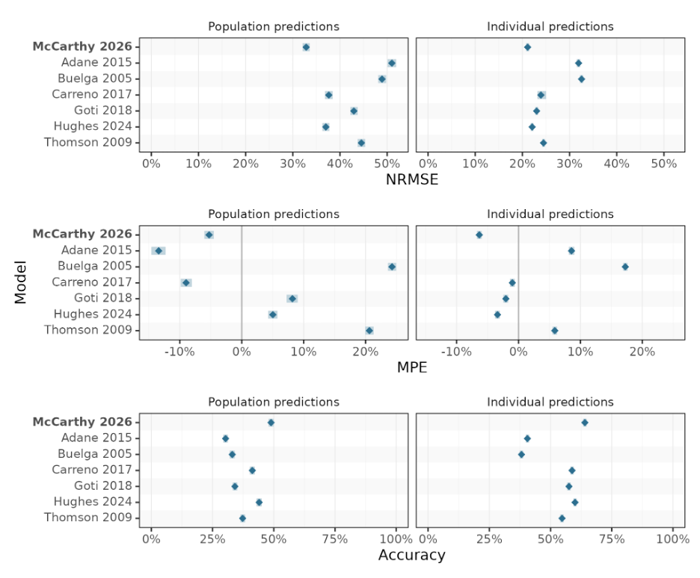
Figure 1: Predictive performance of the McCarthy 2026 model against six published adult vancomycin models available in InsightRX Nova. NRMSE: normalized root mean square error; MPE: mean percent error; Accuracy: percent of predictions within 15% or 2.5 mg/L. Error bars represent the point and the 95% confidence interval estimate for each model. For MPE, the solid vertical line represents a target value of zero bias.
Strategy 3: Modify an existing model without refitting it
A model’s structure and inputs are fixed the day it is published, but the science that informed those choices keeps moving. When that happens, an existing model can often be improved by bringing it in line with the new evidence rather than by refitting it.
For example, the Goti 2018 model follows the common clinical practice of rounding sCr up to 1 mg/dL in patients over 65. The intent was to correct for age-related loss of muscle mass that the Cockcroft-Gault equation does not account for, but evidence has since shown that this rounding underestimates creatinine clearance (CrCL) and leads to inaccurate vancomycin dosing. We put this evidence to the test in an external evaluation of 2,853 elderly patients across 9 US hospital systems: feeding the Goti model raw sCr instead of the age-adjusted value improved its predictions in nearly all patients.
As a second example, in June 2025, the National Kidney Foundation recommended moving from Cockcroft-Gault CrCL to CKD-EPI eGFR for dosing renally-eliminated drugs. However, this guidance did not address model-informed precision dosing, leaving open whether the new equation should be used when applying models built on Cockcroft-Gault CrCL. We tested this substitution in 10,359 adults across 199 US hospital systems: using CKD-EPI eGFR improved predictions in three of five published adult vancomycin models. But this substitution worsened predictions in the two models developed exclusively in patients with obesity, where Cockcroft-Gault CrCL rises much more steeply with body weight than CKD-EPI eGFR does.
In each of these examples, the models themselves were untouched—only their inputs changed. These studies could not have been run at isolated institutions; establishing whether a published model improves under a new input means testing it in enough patients from each subgroup to find where the answer changes, including the groups where this answer turns out to be no. These broad, multi-institutional data sets also provide confidence in transferability of these results to new healthcare organizations. Modified versions of these models are now available to users of InsightRX Nova.
Better models and better selection reinforce each other
Each of these advancements adds to the catalog of models available in InsightRX Nova, which raises the question a clinician actually faces at the bedside: which model should I choose for my patient?
InsightRX Gemini answers this for you by sorting patients into subpopulations according to their sex, age, body size, and kidney function. It then selects the model that has performed best for patients like them, before any vancomycin levels are drawn. Our latest release adds the McCarthy 2026 model and CKD-EPI eGFR versions of the published models that improved with the substitution. Across our evaluation population, these changes improved individual prediction accuracy from 66% to 68%, reduced bias (MPE) from 1.8% to 0.9%, and reduced error (NRMSE) from 28% to 27%.
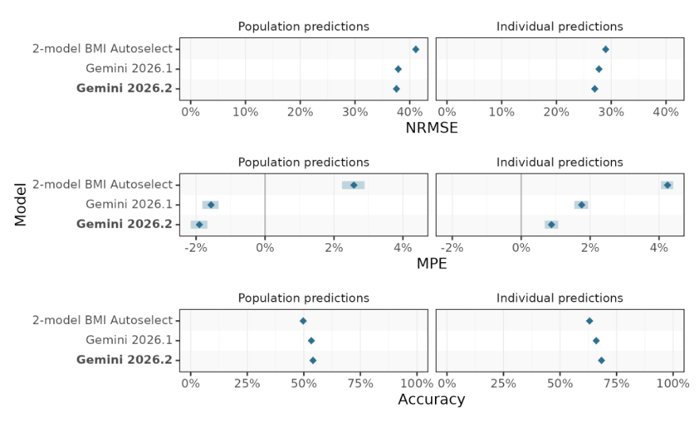
Figure 2: Predictive performance of the new Gemini release (Gemini 2026.2), relative to our March 2026 release (Gemini 2026.1), and to our 2-model algorithm (the Capped Thomson model for patients of BMI < 40 kg/m2 and the Hughes 2024 model for patients with BMI > 40 kg/m2). NRMSE: normalized root mean square error; MPE: mean percent error; Accuracy: percent of predictions within 20% or 2.5 mg/L.
Although these improvements are modest in aggregate, they have changed Gemini's recommendations in ways clinicians will notice. In the previous release, Gemini indicated the Hughes 2024 model—developed in patients with obesity—for several groups of patients who were not obese. The evidence supported it: Hughes really was the best-performing model for patients with these characteristics. But this recommendation was not intuitive, and our users often questioned the suitability of the model for their patients without obesity. A recommendation a clinician cannot rationalize is one they are less likely to act on.
The fix was a better model catalog, not a different algorithm. Gemini still weighs the same evidence, but with the McCarthy 2026 model and the CKD-EPI versions in the pool to serve patients without class III obesity, the Hughes 2024 model is now selected mostly for the patients it was built for.
Recommendation for practice
A model taken from the literature and deployed unchanged is a reasonable place to start. However, in the population of over 600,000 adult vancomycin patients informing InsightRX Gemini, static published models are only the best available option for about 15% of patients. The other 85% are better served by a model we developed ourselves, or by one we have since improved in line with current evidence, which only happens if someone keeps looking after the model is already in production.
What that means for you depends on how you select models:
- Gemini users will automatically receive the latest data-driven model recommendations.
- Clinicians performing manual model selection may wish to consider the following models based on the characteristics of their patients:
- McCarthy 2026 for general adult dosing
- Brooks young adult and low sCr models for patients meeting those criteria
- Tong CRRT model for patients receiving CRRT
- Hughes 2024 for patients with BMI > 40 kg/m2
- The CKD-EPI eGFR version of other general adult models built on Cockcroft-Gault CrCL (though not for models developed exclusively in patients with obesity, which perform best on their original input)
The models in this post were built and tested on deidentified data contributed by hundreds of institutions like yours, and every finding was or will be published so the field benefits too—whether or not it runs on our software. The next generation of models will be built on the data being contributed now: every patient you treat with InsightRX Nova helps you treat the next one better.